Regenerating blood supply, saving limbs.
Transverse Cortical Tibial Transport (TTT) is a bone-transport technique that stimulates new blood vessel growth in the lower limb. Mr Nesbitt leads one of three main centres for TTT in the UK, and the only centre using the technique in patients with critical limb ischaemia and diabetes.

What is Transverse Cortical Tibial Transport?
TTT applies the principles of distraction osteogenesis — the same biological process that underpins limb lengthening with a circular frame — to a different end: regenerating the blood supply to an ischaemic limb.
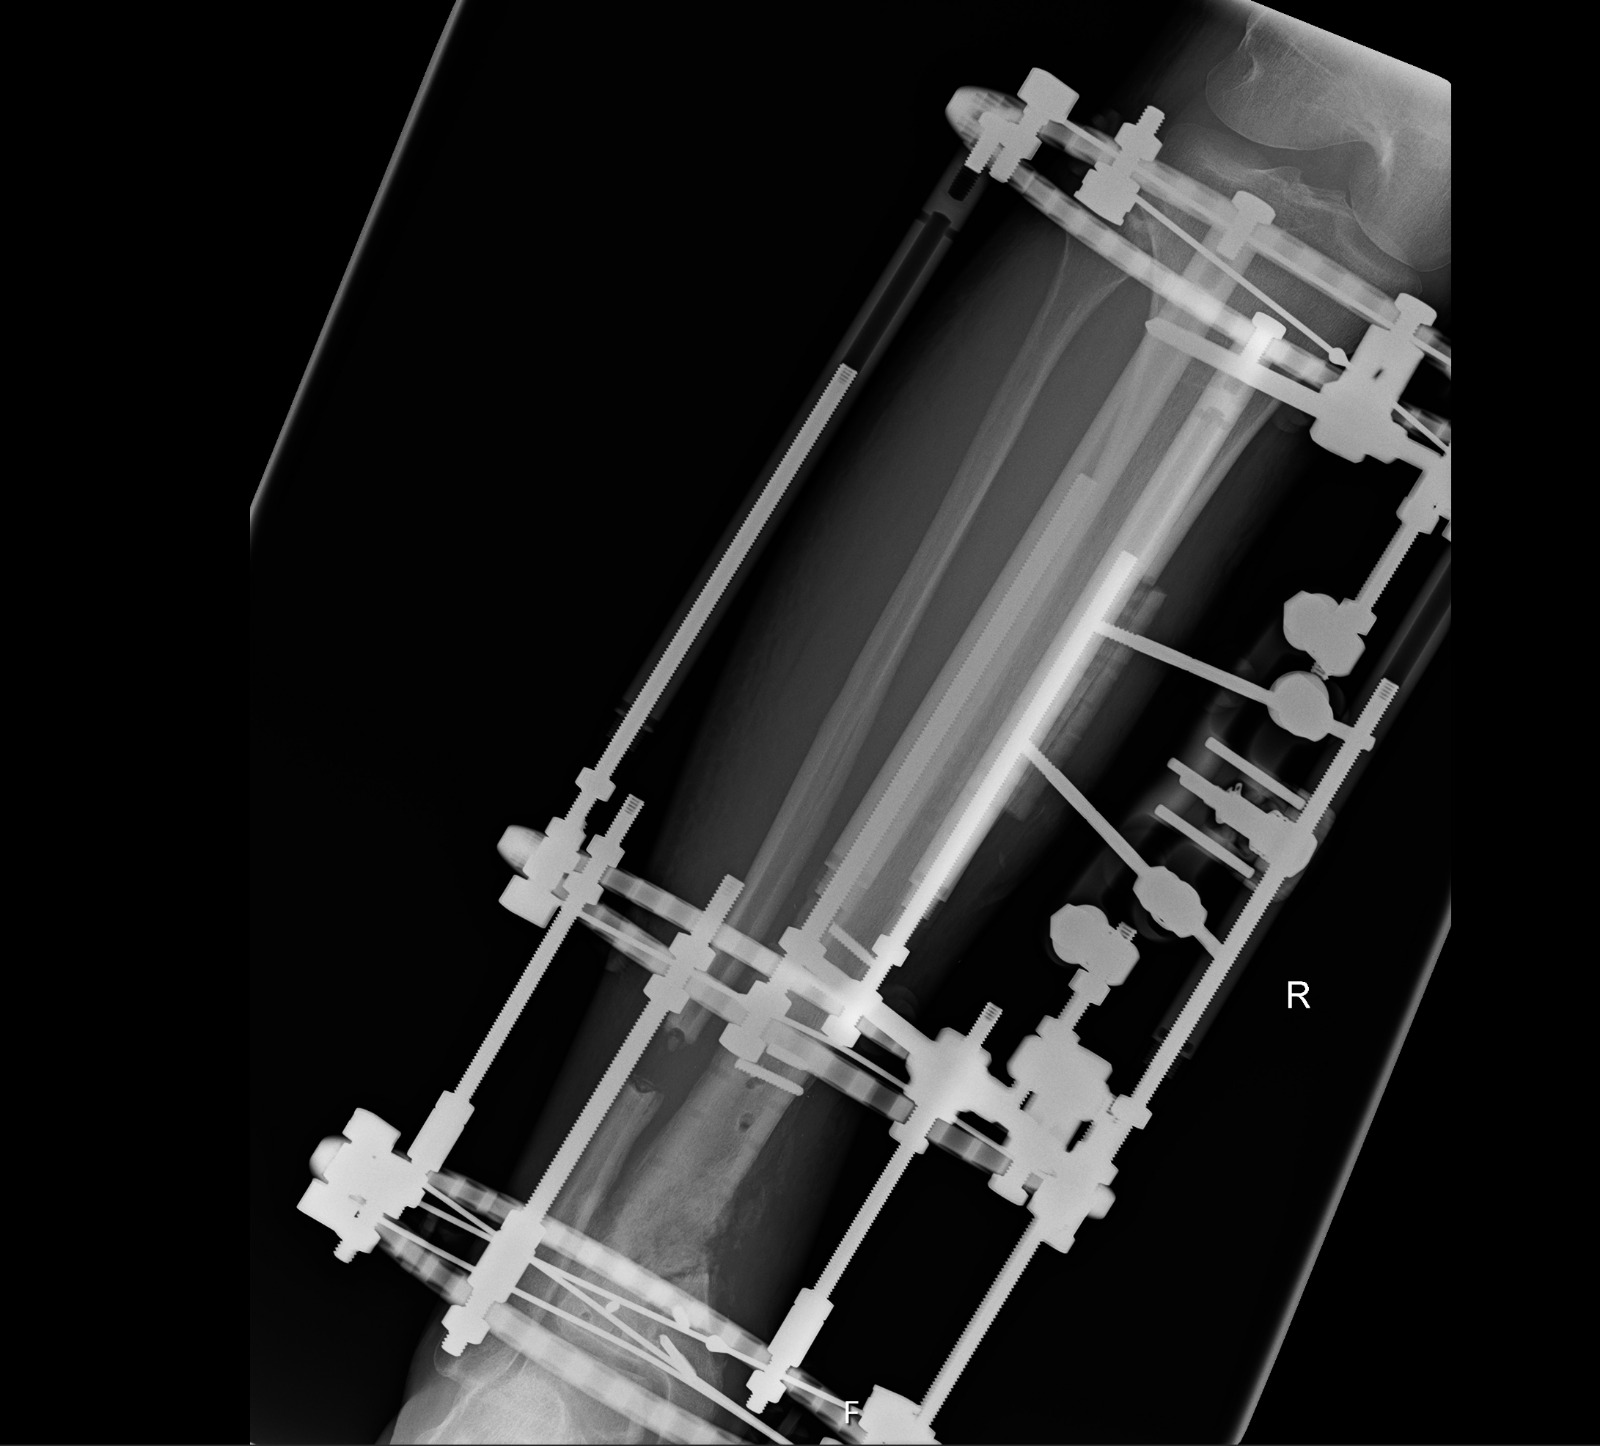
A circular frame is applied to the tibia and a small window of cortical bone is gradually transported across the bone using fine adjustments made daily by the patient or carer, in the same way bone is lengthened during limb reconstruction. Rather than lengthening the limb, this slow transport stimulates the formation of new microvasculature — small new blood vessels that improve perfusion to the surrounding soft tissues, skin and wound bed.
For patients with chronic limb-threatening ischaemia, non-healing diabetic foot ulcers, or severe claudication that has not responded to angioplasty, bypass or best medical therapy, this regenerative effect can mean the difference between progressive deterioration towards amputation and a limb that is salvaged, with a healed wound and improved walking distance.
Manchester is one of three main centres for TTT in the UK, and the only centre using the technique in patients with critical limb ischaemia and diabetes, delivered through a dedicated multi-disciplinary pathway with vascular surgery — meaning patients are assessed jointly, optimised medically and surgically before frame application, and followed up by a team experienced in both reconstruction and vascular disease.
When TTT may help.
TTT is considered for patients with chronic limb-threatening conditions where standard vascular treatment has reached its limit, but the limb remains potentially salvageable. Every referral is assessed jointly by the limb reconstruction and vascular teams.
Diabetic Foot Ulceration
Non-healing diabetic foot ulcers where revascularisation has not restored sufficient perfusion for the wound bed to heal.
Critical Limb Ischaemia
Severe peripheral arterial disease with rest pain, tissue loss or ulceration in patients no longer suitable for angioplasty or bypass.
Chronic Claudication
Debilitating claudication pain that limits walking distance and quality of life despite optimal medical management.
Limb Salvage
An alternative to major amputation in carefully selected patients with a threatened but viable limb.
From referral to recovery.
Every TTT pathway follows the same structured sequence, with the vascular and limb reconstruction teams involved at each stage.
MDT Assessment
Joint review by the vascular and limb reconstruction teams, including imaging and vascular studies, to confirm TTT is appropriate.
Vascular Optimisation
Any reversible vascular issues — angioplasty, bypass or medical optimisation — are addressed first, where appropriate.
Frame Application
A circular frame is applied to the tibia and the corticotomy performed under the same anaesthetic.
Transport Phase
The bone window is transported gradually over several weeks, with regular clinic review to monitor progress and wound healing.
Consolidation & Removal
Once transport is complete and the new blood supply established, the frame is removed and follow-up continues with the vascular team.
Why Manchester.
TTT requires both circular frame expertise and a vascular surgery partnership willing to work jointly through every stage of the pathway. Few units anywhere combine both.
Frequently asked questions.
Answers to the questions most commonly raised by patients, GPs and referring teams about Transverse Cortical Tibial Transport.
What does TTT actually do to the leg?
Who decides if I’m suitable for TTT?
Is the procedure painful?
How long does the whole process take?
What happens if TTT doesn’t improve my circulation?
How is TTT accessed privately?
Will I be able to put weight on my leg during treatment?
Refer or enquire.
Early discussion is welcome for any patient with a chronic wound, critical limb ischaemia or claudication where TTT may be relevant.
Patients, GPs & Consultants
Private assessment for TTT can be arranged at The Alexandra Hospital, Cheadle. You may self-refer or be referred by your GP or consultant. Please include any relevant vascular imaging and a summary of treatment to date with your enquiry.
- HospitalThe Alexandra, Cheadle
- SecretaryOlivia Clowes
- Enquiriespnesbitt@themanchesterframesurgeon.com
Patients, GPs & Consultants
For general questions about TTT, suitability, or to discuss a specific case, please contact the practice secretary, who will direct your enquiry to Mr Nesbitt.
- Secretarypnesbitt@themanchesterframesurgeon.com
- PrivateThe Alexandra Hospital, Cheadle
- InsurersMajor UK insurers recognised